Atlas (C1 - First Cervical Vertebra)
Atlas (C1)
Overview
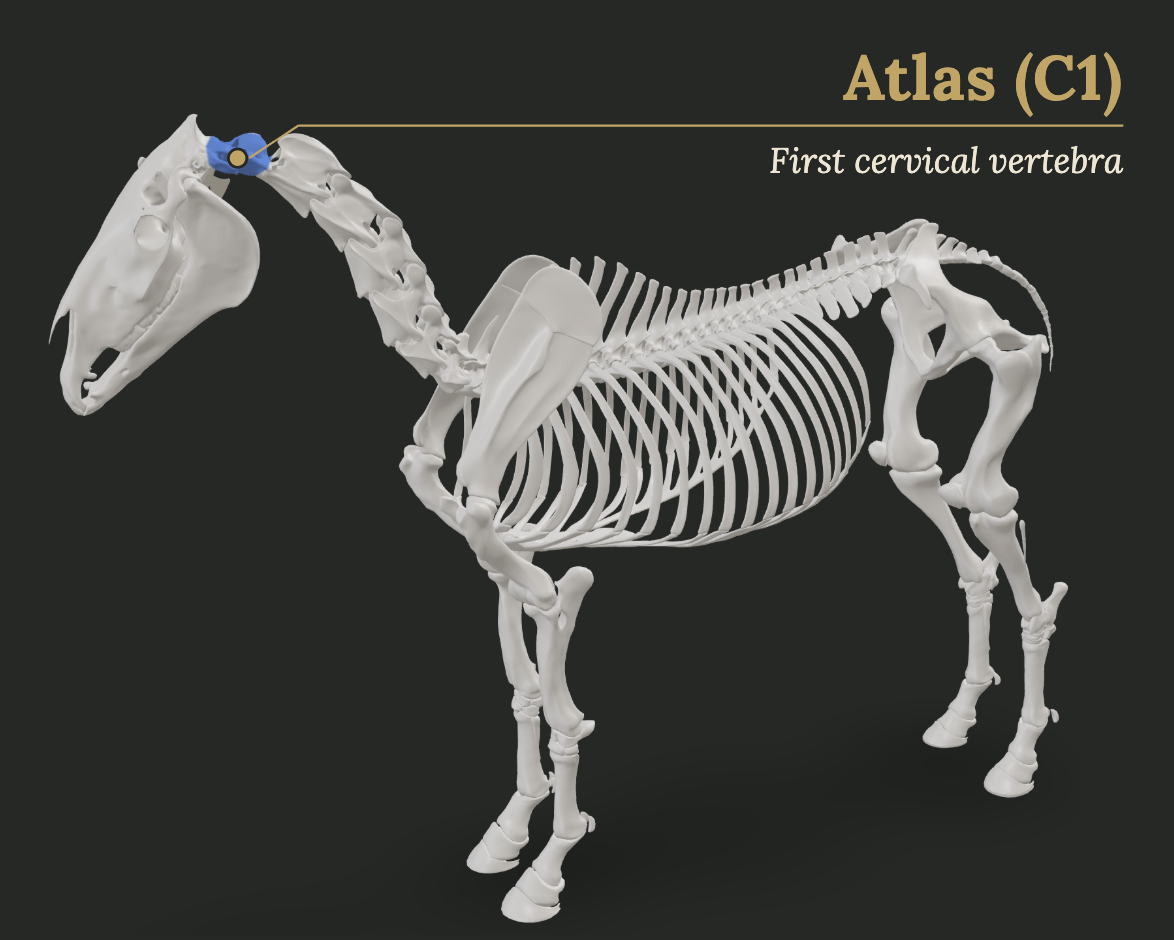
The atlas (C1) is the first cervical vertebra, a ring-shaped bone with no body or spinous process. Its wide transverse processes (wings) are palpable behind the jaw and anchor head-stabilizing muscles. The cranial articular surfaces cradle the occipital condyles for nodding; the caudal surfaces articulate with the axis for rotation.
Anatomical Details
Origin: N/A (bone)
Insertion: N/A (bone)
Action: Support the head and neck; allow flexion, extension, lateral bending, and rotation; the neck acts as a balancing rod during locomotion
Clinical Significance
Relevant conditions: occipito-atlanto-axial malformation (OAAM, especially Arabians), atlas fracture (wing or arch), atlanto-occipital luxation. Imaging: radiographs, CT. Fractures can be conservatively managed if stable; OAAM prognosis is generally poor.
Common Conditions & Injuries
Atlas fracture
## Overview Fracture of the atlas (first cervical vertebra) is an uncommon traumatic injury. The atlas lacks a vertebral body and consists of a ring with broad wings; fractures may involve the dorsal
Atlanto-occipital malformation (OAAM)
## Overview Occipitoatlantoaxial malformation (OAAM) is a congenital developmental defect in which the occipital bone, atlas, and axis are abnormally formed and often fused. The malformation narrows
Atlanto-axial subluxation
## Overview Atlanto-axial subluxation is partial dislocation of the joint between the first cervical vertebra (atlas) and the second cervical vertebra (axis). It may be congenital or, more often in a
What Horse Owners Should Know
Head tilt, resistance to bridling, or difficulty flexing at the poll may point to atlas problems. After any head or neck trauma, stabilize the horse and call a vet immediately.
Frequently Asked Questions
What is Atlas fracture in horses?
## Overview Fracture of the atlas (first cervical vertebra) is an uncommon traumatic injury. The atlas lacks a vertebral body and consists of a ring with broad wings; fractures may involve the dorsal arch, wings, or articular surfaces. Neurologic signs depend on fragment displacement into the spinal canal. Foals are more susceptible than adults because of incomplete ossification. ## Causes Falls over backward, collisions, and kicks are the usual causes. Hyperflexion or hyperextension of the cranial neck transmits force to the atlas. ## Diagnosis Acute neck pain, swelling, abnormal head carriage, and variable ataxia follow trauma. Radiographs may reveal the fracture, but computed tomography is often required for complete characterization, especially of minimally displaced or articular fractures. ## Treatment Stable, minimally displaced fractures are managed with stall rest and anti-inflammatory medication. Unstable fractures or those causing progressive neurologic deficits may require surgical stabilization when feasible. External coaptation is rarely practical in adult horses. ## Recovery and Prognosis Prognosis correlates with the degree of spinal-cord compression and fracture stability. Horses with minimal displacement and no or mild ataxia can recover fully. Severe cord damage carries a guarded to grave prognosis. ## Prevention Minimizing situations that lead to falls over backward or high-speed collisions. Signs include: acute neck pain after trauma; swelling over the poll or cranial neck; abnormal head carriage; ataxia of variable severity
What is Atlanto-occipital malformation (OAAM) in horses?
## Overview Occipitoatlantoaxial malformation (OAAM) is a congenital developmental defect in which the occipital bone, atlas, and axis are abnormally formed and often fused. The malformation narrows the spinal canal and compresses the upper cervical spinal cord. It is most frequently recognized in Arabian horses and is inherited as an autosomal recessive trait in at least one form (OAAM1) linked to a deletion near the HOXD3 gene. Clinical signs are present at birth or appear in the first months of life. ## Causes OAAM1 is caused by a 2.7 kb deletion near HOXD3. Other genetic or developmental causes exist in Arabians and other breeds (Miniature Horses, Quarter Horses, Friesians). The precise embryologic mechanism involves failure of normal segmentation of the cranial cervical sclerotomes. ## Diagnosis Foals show abnormal head and neck carriage (often extended), neck stiffness, progressive ataxia, and sometimes an audible click with neck movement. Radiographs reveal occipitalization of the atlas, fusion, and spinal-canal stenosis. Genetic testing identifies carriers and affected animals for the OAAM1 variant. ## Treatment No corrective treatment exists. Supportive care and restricted activity may be tried in mildly affected animals, but most foals with significant neurologic deficits are euthanized. ## Recovery and Prognosis Prognosis is poor for athletic use or normal quality of life when neurologic signs are present. Mildly affected horses occasionally survive but remain neurologically compromised. ## Prevention Genetic testing of Arabian breeding stock and avoidance of carrier-to-carrier matings prevent OAAM1. Testing is recommended for Arabians and Arabian crosses. Signs include: abnormal head and neck carriage from birth; neck stiffness or extended posture; progressive ataxia; reluctance to move the neck; occasional clicking sound
What is Atlanto-axial subluxation in horses?
## Overview Atlanto-axial subluxation is partial dislocation of the joint between the first cervical vertebra (atlas) and the second cervical vertebra (axis). It may be congenital or, more often in adults, the result of trauma that disrupts the ligaments stabilizing the dens. The subluxation can compress the spinal cord, producing ataxia or neck pain and stiffness. True luxation (complete dislocation) is rarer and more severe. ## Causes Trauma from falls, rearing and falling backward, or collisions is the usual cause in mature horses. Congenital forms exist but are less commonly reported than occipitoatlantoaxial malformation. Ligamentous failure allows ventral or lateral displacement of the axis relative to the atlas. ## Diagnosis Clinical signs include neck stiffness, abnormal head carriage, reluctance to flex or extend the neck, and variable ataxia. Radiographs demonstrate malalignment; standing computed tomography provides superior detail of the dens and articular relationships. Neurologic examination quantifies spinal-cord compromise. ## Treatment Mild, stable subluxations may be managed with stall rest and anti-inflammatory medication. Unstable or significantly displaced cases require surgical reduction and stabilization when feasible. Closed reduction under general anesthesia has been successful in selected adult horses. ## Recovery and Prognosis Prognosis depends on the degree of spinal-cord compression and the stability achieved. Horses with minimal neurologic deficits and successful reduction can return to work. Severe cord damage or irreducible instability carries a guarded to poor prognosis. ## Prevention No specific prevention beyond minimizing traumatic incidents. Signs include: neck pain or stiffness; abnormal head carriage; reluctance to move the neck; ataxia; audible click in some cases
What are the clinical concerns for the Atlas (C1 - First Cervical Vertebra)?
Relevant conditions: occipito-atlanto-axial malformation (OAAM, especially Arabians), atlas fracture (wing or arch), atlanto-occipital luxation. Imaging: radiographs, CT. Fractures can be conservatively managed if stable; OAAM prognosis is generally poor.
What should horse owners know about the Atlas (C1 - First Cervical Vertebra)?
Head tilt, resistance to bridling, or difficulty flexing at the poll may point to atlas problems. After any head or neck trauma, stabilize the horse and call a vet immediately.
Explore This Structure in 3D
See the Atlas (C1 - First Cervical Vertebra) on our interactive 3D horse model. Open 3D Model