Axis (C2 - Second Cervical Vertebra)
Axis (Epistropheus, C2)
Overview
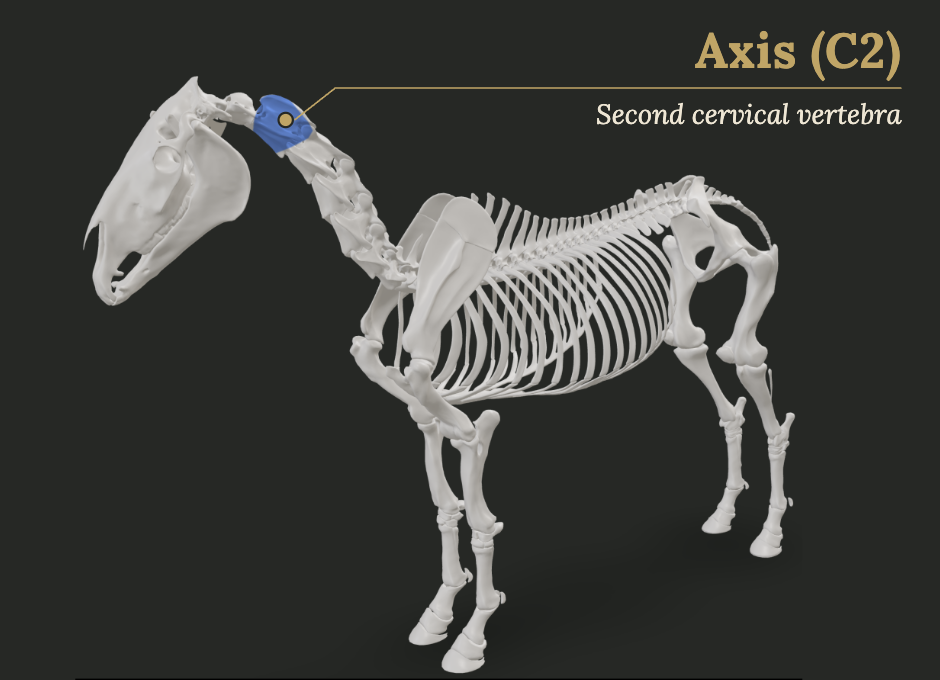
The axis (C2) is the longest cervical vertebra, specialized for head rotation. Its dens (tooth-like projection) extends into the atlas as a pivot point. The tall dorsal crest anchors the nuchal ligament and powerful neck muscles.
Anatomical Details
Origin: N/A (bone)
Insertion: N/A (bone)
Action: Support the head and neck; allow flexion, extension, lateral bending, and rotation; the neck acts as a balancing rod during locomotion
Clinical Significance
Relevant conditions: dens fracture, atlanto-axial subluxation, OAAM (axis often "atlantized"), vertebral osteomyelitis. Imaging: radiographs, CT, myelography. Prognosis varies with neurologic grade.
Common Conditions & Injuries
Cervical vertebral fracture / instability
## Overview This entry covers cervical vertebral fractures that produce instability, meaning the vertebrae can shift abnormally and threaten the spinal cord. Instability may be immediate after trauma
Rib fracture
## Overview Rib fractures result from kicks, falls, or compression (foals stepped on by mares). They cause localized pain, swelling, shallow rapid breathing, and reluctance to expand the chest. Displ
Sacroiliac joint disease
Sacroiliac joint disease involves pain and dysfunction in the joint where the sacrum meets the pelvis. It is one of the most common causes of poor hindlimb impulsion and performance problems in sport
Vertebral body osteomyelitis
## Overview Vertebral body osteomyelitis is bacterial infection of a vertebral body. It is most common in foals (often Rhodococcus equi) or from hematogenous spread in adults. Signs include fever, st
Spondylosis deformans
## Overview Spondylosis deformans is the formation of bridging bone spurs between adjacent vertebral bodies. It is often an incidental finding in older horses on radiographs or at necropsy. Extensive
Axis fracture / dens fracture
## Overview Fracture of the axis (second cervical vertebra), particularly of the dens (odontoid process), is a serious traumatic injury. In foals the fracture often occurs through the dens growth pla
Wobbler Syndrome
Wobbler syndrome, also known as cervical vertebral stenotic myelopathy, is a neurologic condition caused by compression of the spinal cord in the neck. It leads to progressive incoordination (ataxia),
Kissing spines
Kissing spines, also known as overriding dorsal spinous processes, occur when the bony projections along the top of the horse's spine touch or overlap, causing pain and inflammation. This condition mo
What Horse Owners Should Know
Stiffness, reluctance to bend the neck, or incoordination after a fall should be evaluated immediately. In foals or young Arabians, abnormal neck posture may indicate developmental malformation involving the axis.
Frequently Asked Questions
What is Cervical vertebral fracture / instability in horses?
## Overview This entry covers cervical vertebral fractures that produce instability, meaning the vertebrae can shift abnormally and threaten the spinal cord. Instability may be immediate after trauma or develop as fragments displace. Clinical signs are those of fracture plus varying degrees of ataxia or paresis. ## Causes Trauma that disrupts bony or ligamentous stabilizers of the cervical spine. ## Diagnosis Neurologic examination plus imaging (radiographs, computed tomography) that demonstrates malalignment or excessive motion. Dynamic views are used cautiously. ## Treatment Strict immobilization, anti-inflammatory medication, and, when appropriate, surgical stabilization. Prognosis is poorer than for stable fractures. ## Recovery and Prognosis Guarded to poor. Successful surgical cases exist, but many horses do not regain athletic function or survive. ## Prevention Same as for cervical fracture. Signs include: neck pain; ataxia; paresis; abnormal vertebral alignment on imaging; worsening neurologic signs
What is Rib fracture in horses?
## Overview Rib fractures result from kicks, falls, or compression (foals stepped on by mares). They cause localized pain, swelling, shallow rapid breathing, and reluctance to expand the chest. Displaced fragments can lacerate the lung, causing pneumothorax, or damage intercostal arteries. Crepitus may be felt. ## Causes Blunt trauma. ## Diagnosis Palpation, ultrasound, and radiographs. ## Treatment Pain control and rest for simple fractures. Emergency management of pneumothorax or hemothorax if present. Most uncomplicated fractures heal with time. ## Recovery and Prognosis Good for simple fractures. Complications worsen the outlook. ## Prevention Safe environments, especially for foals. Signs include: localized pain and swelling over the ribs; pain on breathing; shallow rapid breathing; crepitus; possible pneumothorax
What is Sacroiliac joint disease in horses?
Sacroiliac joint disease involves pain and dysfunction in the joint where the sacrum meets the pelvis. It is one of the most common causes of poor hindlimb impulsion and performance problems in sport horses. The condition can result from strain, subluxation, or osteoarthritis of the sacroiliac joint and its supporting ligaments. ## What it is The sacroiliac joints are low-motion synovial joints that transfer propulsive forces from the hindlimbs to the axial skeleton. Strong ligaments surround the joints and provide stability. Dysfunction can arise from acute trauma, repetitive stress, poor conformation, or degenerative changes. The joint is difficult to image directly, so diagnosis often relies on clinical signs, response to diagnostic analgesia, and exclusion of other causes of hindlimb lameness. ## Signs and symptoms - Poor hindlimb impulsion and engagement - Hunter's bump (prominent tuber sacrale on one or both sides) - Asymmetric gluteal muscle development - Difficulty with collection, lateral work, or jumping - Pain on palpation or manipulation of the sacroiliac region - Cross-cantering or reluctance to canter on one lead - Chronic cases may show muscle atrophy or compensatory back pain ## Causes and risk factors Sacroiliac joint disease is often associated with repetitive stress in sport horses, conformational issues (especially asymmetry), poor saddle fit, and previous trauma. Young horses in intense training and horses with weak core muscles appear to be at higher risk. The condition can also develop secondary to other sources of pain that alter gait mechanics. ## How it is diagnosed Diagnosis is challenging and usually involves a combination of clinical examination, palpation, and diagnostic analgesia (blocking the sacroiliac region). Radiographs and ultrasound have limited value for the joint itself but can rule out other problems. Nuclear scintigraphy (bone scan) is often helpful for identifying increased uptake in the sacroiliac region. A positive response to local anesthesia in the sacroiliac area supports the diagnosis. ## Treatment and management Treatment typically includes a period of rest or modified exercise, physiotherapy and core strengthening, shockwave therapy, and anti-inflammatory medication. Some horses benefit from sacroiliac joint injections (corticosteroids or regenerative therapies). Long-term management focuses on improving core strength, correcting any saddle fit issues, and addressing conformational or biomechanical contributors. Many horses can return to previous levels of work with appropriate management. ## When to call the vet Contact your veterinarian if your horse shows persistent poor impulsion, asymmetric muscle development, or resistance to collection that does not improve with basic training adjustments. Early intervention often leads to better outcomes. ## Prevention Prevention focuses on maintaining good core strength and symmetry through appropriate conditioning, ensuring proper saddle fit, and avoiding sudden increases in workload. Regular assessment of young horses in training can help identify issues early. ## Frequently asked questions **Is sacroiliac joint disease the same as kissing spines?** No, but the two conditions can occur together and both cause back pain and poor performance. **Can a horse with sacroiliac joint disease still compete?** Many horses return to successful competition with proper management, though some require ongoing treatment and modified training. **How long does recovery take?** Recovery timelines vary. Some horses improve significantly within weeks of targeted treatment, while others require months of rehabilitation. This information is for educational purposes only. Always consult with a licensed veterinarian for diagnosis and treatment of your horse. Signs include: Poor hindlimb impulsion and engagement; hunter's bump (prominent tuber sacrale on one or both sides); asymmetric gluteal muscle development; difficulty with collection, lateral work, or jumping; pain on palpation or manipulation of the sacroiliac region; cross-cantering or reluctance to canter on one lead; chronic cases may show muscle atrophy or compensatory back pain
What is Vertebral body osteomyelitis in horses?
## Overview Vertebral body osteomyelitis is bacterial infection of a vertebral body. It is most common in foals (often Rhodococcus equi) or from hematogenous spread in adults. Signs include fever, stiffness, reluctance to move, pain on spinal palpation, and progressive neurologic deficits if the spinal cord is compressed. White blood cell count is elevated. ## Causes Bacterial seeding, frequently Rhodococcus equi in foals. ## Diagnosis Radiographs, computed tomography, or magnetic resonance imaging, plus bloodwork and culture. ## Treatment Prolonged antibiotics. Surgery if there is abscess or cord compression. Prognosis is guarded. ## Recovery and Prognosis Guarded, especially once neurologic signs appear. ## Prevention Rhodococcus control on endemic farms. Signs include: fever; stiffness; reluctance to move; pain on spinal palpation; progressive neurologic deficits; elevated white blood cell count
What is Spondylosis deformans in horses?
## Overview Spondylosis deformans is the formation of bridging bone spurs between adjacent vertebral bodies. It is often an incidental finding in older horses on radiographs or at necropsy. Extensive bridging may reduce spinal flexibility and contribute to back stiffness, but many horses show no clinical signs. ## Causes Age-related degeneration or previous instability. ## Diagnosis Radiographs showing ventral bridging osteophytes. ## Treatment None if asymptomatic. Management of stiffness if clinical. ## Recovery and Prognosis The bony changes are permanent but often not limiting. ## Prevention None. Signs include: often asymptomatic; may cause back stiffness if extensive; reduced spinal flexibility; usually incidental on radiographs
What is Axis fracture / dens fracture in horses?
## Overview Fracture of the axis (second cervical vertebra), particularly of the dens (odontoid process), is a serious traumatic injury. In foals the fracture often occurs through the dens growth plate; in adults mid-body or cranial fractures result from hyperflexion. Displacement can compress the spinal cord, producing ataxia, paresis, or sudden death. The physis of the dens closes between 8 and 12 months of age. ## Causes Falls over backward, collisions, and hyperflexion injuries (for example, during jumping or racing) are the usual causes. The ligamentous attachments of the dens transmit force that can avulse or fracture the process. ## Diagnosis Acute neurologic signs or neck pain after trauma raise suspicion. Radiographs may show dens displacement or a mid-body fracture line. Computed tomography provides definitive characterization and assesses spinal-canal compromise. ## Treatment Minimally displaced fractures in foals have been successfully repaired with surgical reduction and stabilization. Adult mid-body fractures may be managed with locking-plate fixation in selected cases. Conservative management is appropriate only for stable, non-displaced fractures without neurologic deficits. ## Recovery and Prognosis Prognosis is guarded and depends on the degree of cord compression and the success of stabilization. Foals treated promptly for dens physeal fractures can recover good function. Severe displacement or delayed treatment worsens the outlook. ## Prevention Avoidance of situations leading to falls over backward or extreme neck hyperflexion. Signs include: acute ataxia or paresis after trauma; neck pain; abnormal head carriage; recumbency in severe cases; sudden death possible
What is Wobbler Syndrome in horses?
Wobbler syndrome, also known as cervical vertebral stenotic myelopathy, is a neurologic condition caused by compression of the spinal cord in the neck. It leads to progressive incoordination (ataxia), primarily in the hind limbs. There are two main forms: Type I (dynamic compression in young horses) and Type II (static compression in older horses due to osteoarthritis). ## What it is In Type I wobbler syndrome, developmental abnormalities of the cervical vertebrae cause narrowing of the vertebral canal and dynamic compression of the spinal cord during neck movement. It typically affects horses between 1 and 4 years of age, most commonly at C3 to C5. Type II wobbler involves static compression from osteoarthritic enlargement of the articular facets, usually affecting older horses at C5 to C7. Both forms result in damage to the spinal cord, leading to proprioceptive deficits and ataxia that is usually worse in the hind limbs. ## Signs and symptoms - Progressive hindlimb incoordination and ataxia - Wide-based stance and stumbling, especially when turning or going downhill - Toe dragging and difficulty backing - Neck stiffness or pain in some cases - In severe cases, weakness or falling - Symmetric or slightly asymmetric ataxia that is worse in the hind limbs than forelimbs - Positive cervical flexion test in many cases ## Causes and risk factors Type I wobbler is developmental and linked to rapid growth, genetic factors, and nutritional imbalances (especially copper deficiency or excess protein/calcium in young horses). Type II is associated with chronic wear and osteoarthritis of the cervical facet joints. Risk factors include large body size, rapid growth rates in young horses, and conformational issues that place abnormal stress on the neck. ## How it is diagnosed Diagnosis is based on clinical neurologic examination and confirmed with radiographs and myelography or MRI. Standing or recumbent radiographs can show vertebral canal narrowing or facet joint changes. Myelography or MRI provides the most accurate assessment of spinal cord compression. A neurologic grading system helps quantify the severity of ataxia. ## Treatment and management Treatment depends on the type, severity, and age of the horse. Conservative management includes stall rest, anti-inflammatory medication, and controlled exercise. For young horses with Type I, dietary management and restricted growth may help. Surgical options (ventral interbody fusion or dorsal laminectomy) are available for selected cases and can improve neurologic function in many horses. Prognosis varies widely depending on the severity and duration of compression before treatment. ## When to call the vet Contact your veterinarian promptly if your horse shows incoordination, stumbling, or difficulty backing or turning. Early diagnosis improves the chance of successful management or surgical intervention. ## Prevention For Type I wobbler in young horses, prevention focuses on balanced nutrition (avoiding excessive protein and calcium while ensuring adequate copper and other minerals) and avoiding overly rapid growth rates. Regular monitoring of at-risk young horses can help with early detection. ## Frequently asked questions **Can a horse with wobbler syndrome be ridden?** Many horses with mild to moderate signs can be ridden carefully after treatment, but those with severe ataxia are usually retired for safety reasons. **Is surgery always successful for wobbler syndrome?** Surgical success rates are good in appropriately selected cases, but results vary depending on the severity and chronicity of spinal cord damage. **Is wobbler syndrome hereditary?** There is a genetic component, especially in Type I. Breeding horses with wobbler syndrome or from lines with high incidence is generally discouraged. This information is for educational purposes only. Always consult with a licensed veterinarian for diagnosis and treatment of your horse. Signs include: Progressive hindlimb incoordination and ataxia; wide-based stance and stumbling, especially when turning or going downhill; toe dragging and difficulty backing; neck stiffness or pain in some cases; in severe cases, weakness or falling; symmetric or slightly asymmetric ataxia worse in hind limbs; positive cervical flexion test in many cases
What is Kissing spines in horses?
Kissing spines, also known as overriding dorsal spinous processes, occur when the bony projections along the top of the horse's spine touch or overlap, causing pain and inflammation. This condition most commonly affects the thoracolumbar region (T13 to L2) and is seen on radiographs in 30 to 40% of horses, though not all show clinical signs. It is a frequent cause of back pain and poor performance in sport horses. ## What it is The dorsal spinous processes are the upward-pointing bony projections of the vertebrae. In kissing spines, these processes are too close together and impinge on each other during movement, leading to bone remodeling, inflammation of the interspinous ligaments, and pain. The condition is often associated with poor posture, weak core muscles, or conformational factors that increase extension of the back. While many horses have radiographic changes without pain, clinical kissing spines cause significant discomfort, especially under saddle. ## Signs and symptoms - Back pain or sensitivity when pressure is applied along the spine - Dipping away from pressure or hollowing the back under rider - Bucking, rearing, or resistance to collection - Poor performance or unwillingness to go forward - Muscle atrophy along the topline - Reluctance to canter or perform lateral movements - Extreme sensitivity at specific vertebral levels during grooming or saddling - Cross-cantering or difficulty maintaining a consistent gait ## Causes and risk factors Kissing spines develop from a combination of conformational, biomechanical, and management factors. Risk factors include weak abdominal and back muscles, repetitive extension of the spine (common in jumping and dressage), poor saddle fit, and genetic predisposition. Horses with long backs or weak toplines are more susceptible. The condition can also develop secondary to other sources of pain that cause the horse to hollow its back. ## How it is diagnosed Diagnosis combines clinical examination, palpation of the back, and imaging. Radiographs are the primary tool and show the proximity or overlap of the spinous processes. Nuclear scintigraphy (bone scan) can help identify active inflammation. Ultrasound evaluates the interspinous ligaments and soft tissues. Local anesthesia of the affected interspinous spaces is often used to confirm that the kissing spines are the source of pain. ## Treatment and management Treatment options range from conservative to surgical. Conservative management includes physiotherapy, core strengthening exercises, shockwave therapy, mesotherapy, and anti-inflammatory medication. Interspinous ligament injections or corticosteroid injections into affected spaces can provide relief. In refractory cases, surgical options such as interspinous ligament desmotomy or partial resection of the spinous processes are used with good success rates in appropriately selected horses. Saddle fit evaluation and rehabilitation are essential components of long-term management. ## When to call the vet Contact your veterinarian if your horse shows signs of back pain, resistance under saddle, or performance issues that do not resolve with basic management changes. Early diagnosis and a multimodal treatment plan offer the best chance of returning the horse to comfortable work. ## Prevention Prevention focuses on maintaining strong core and back muscles through appropriate conditioning and avoiding repetitive spinal extension without adequate strength. Regular saddle fit checks, good footing, and prompt attention to any signs of back discomfort help reduce risk. Horses with conformational risk factors benefit from proactive core strengthening programs. ## Frequently asked questions **Do all horses with kissing spines on X-rays have pain?** No. Many horses have radiographic changes without clinical signs. Diagnosis requires correlation with clinical findings and response to local anesthesia. **Can kissing spines be cured?** Surgical treatment can provide long-term improvement in many horses. Conservative management can control symptoms but may not eliminate the underlying bony changes. **Is surgery always necessary?** No. Many horses respond well to physiotherapy, injections, and rehabilitation. Surgery is usually reserved for cases that do not improve with conservative treatment. This information is for educational purposes only. Always consult with a licensed veterinarian for diagnosis and treatment of your horse. Signs include: Back pain or sensitivity when pressure is applied along the spine; dipping away from pressure or hollowing the back under rider; bucking, rearing, or resistance to collection; poor performance or unwillingness to go forward; muscle atrophy along the topline; reluctance to canter or perform lateral movements; extreme sensitivity at specific vertebral levels during grooming or saddling; cross-cantering or difficulty maintaining a consistent gait
What are the clinical concerns for the Axis (C2 - Second Cervical Vertebra)?
Relevant conditions: dens fracture, atlanto-axial subluxation, OAAM (axis often "atlantized"), vertebral osteomyelitis. Imaging: radiographs, CT, myelography. Prognosis varies with neurologic grade.
What should horse owners know about the Axis (C2 - Second Cervical Vertebra)?
Stiffness, reluctance to bend the neck, or incoordination after a fall should be evaluated immediately. In foals or young Arabians, abnormal neck posture may indicate developmental malformation involving the axis.
Explore This Structure in 3D
See the Axis (C2 - Second Cervical Vertebra) on our interactive 3D horse model. Open 3D Model